
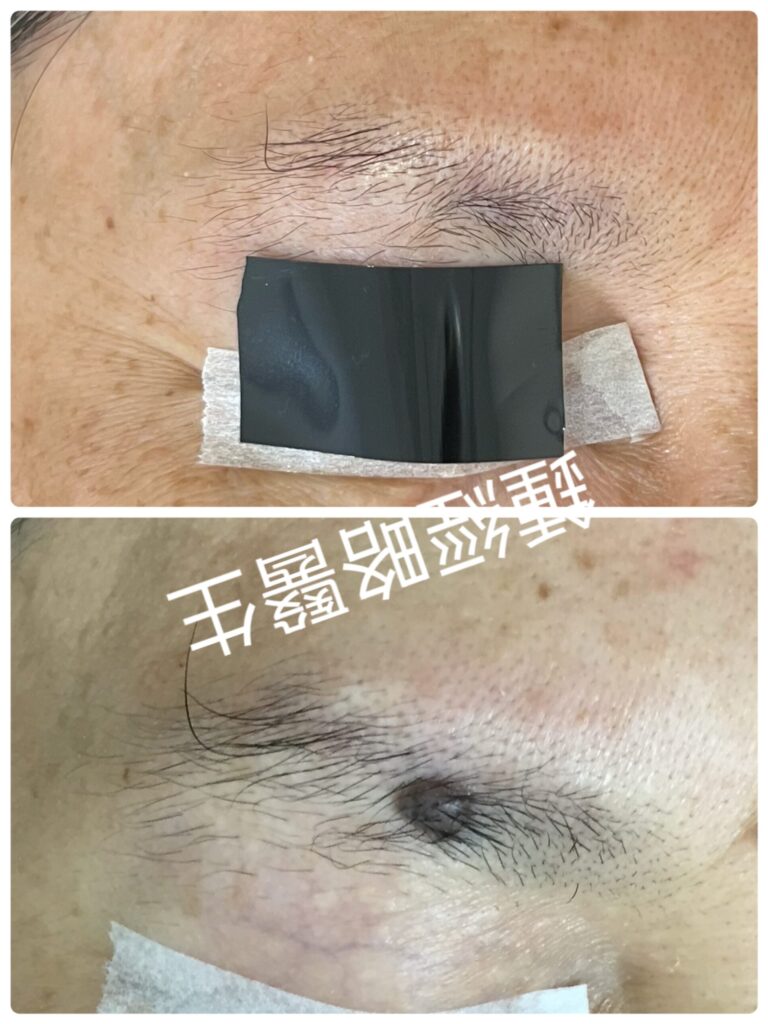
Case Presentation
A 65-year-old male requested the removal of a long-standing right eyebrow mole for cosmetic reasons. He has an unremarkable medical history, no significant family history, and takes no long-term medications.
The lesion has been present since age 15. The patient reported no recent changes in size, shape, color, or symmetry. Furthermore, he noted no pain, tenderness, itching, spontaneous bleeding, or ulceration.
Physical Examination
Clinical inspection revealed a classic, highly benign intradermal nevus situated within the right eyebrow.
- Dimensions: 0.5 cm times 0.6 cm, elevated 0.4 cm above the skin surface.
- Morphology: Oval, sharply demarcated, well-circumscribed, and perfectly symmetrical.
- Color & Surface: Uniformly dark brown to black, homogeneous pigment distribution, smooth contour, intact skin markings, and complete absence of ulceration, crusting, or satellite lesions.
- Associated Structures: Terminal eyebrow hairs naturally emerged from the surface of the mole, further confirming its benign nature.
Management & Surgical Technique
Given the clinical findings, we confirmed a benign intradermal nevus. Therefore, we proceeded with direct CO laser ablation without histological examination.
- Anesthesia: We infiltrated a small volume of local anesthetic beneath the lesion.
- Layer-by-Layer Ablation: Under 5.0 times operational loupe magnification, we precisely vaporized the mole layer by layer. The high magnification allowed us to clearly visualize the melanocyte nests (“roots”) throughout the procedure.
- Thermal Management: We continuously wiped away carbonized debris. As a result, the procedure produced virtually no char and zero intraoperative bleeding.
- Endpoint Identification: We stopped ablation as soon as we reached a clean, non-pigmented dermal floor.
Visual Endpoint Findings
The final laser bed formed a neat, depressed wound. Crucially, intact, viable hair follicle bulbs remained clearly visible across the floor of the defect. Because the laser spared these deep follicular structures, we anticipated complete hair regrowth provided we prevented severe post-operative inflammation.
Post-Operative Care & Clinical Outcome
To ensure optimal secondary intention healing, the patient followed a strict post-operative regimen:
- Cleaned the wound with an antiseptic solution several times daily for 2 weeks.
- Kept the wound dry and strictly avoided direct water exposure during early epithelialization.
Outcome
The wound healed rapidly via secondary intention. Within 6 to 8 months, local erythema faded, and skin color returned entirely to normal. Most importantly, all eyebrow hairs grew back completely with zero hair loss. Today, the residual scar is almost unnoticeable.
Discussion
Achieving an optimal outcome when removing an intra-eyebrow mole requires balancing depth control, follicular preservation, and scar aesthetics.
First, the clinician must accurately judge the depth of the laser defect. If a mole extends so deeply that secondary intention healing would cause a noticeable indented scar, primary suturing becomes necessary.
Second, preserving hair follicles is paramount. If laser ablation destroys the local hair follicles, secondary intention healing will leave a permanent bald patch within the eyebrow. In such deep cases, a surgeon should suture the wound after laser ablation. Primary closure neatly hides the linear scar within the natural flow of the eyebrow hair.
Finally, practitioner expertise directly dictates the outcome. Combining dermatological knowledge with aesthetic refinement allows a clinician to accurately judge the visual endpoint, protect delicate hair follicles, and select the correct closure method. Consequently, a physician with formal postgraduate training in both dermatology (eg MSc Clinical Dermatology) and aesthetic medicine (eg MSc Aesthetic Medicine) is ideally suited for this delicate procedure.
病例匯報(Case Presentation)
一名 65 歲男性因美容考量,要求切除長於右側眉毛內多年的墨痣。患者過往健康狀況良好,無特殊家族病史,亦無長期服用任何藥物。
該病灶自患者 15 歲起便已存在。患者表示近年病灶在大小、形狀、顏色或對稱性上均無變化。此外,病灶無疼痛、壓痛、瘙癢、自發性出血或潰爛。
體格檢查(Physical Examination)
臨床檢查顯示右側眉毛內有一典型且極具良性特徵的皮內痣(Intradermal nevus):
- 尺寸: 0.5 cm times 0.6 cm,高出皮膚表面 0.4 cm。
- 形態: 呈橢圓形,邊界清晰,輪廓分明,且完全對稱。
- 顏色與表面: 呈均勻的深棕色至黑色,色素分佈均勻,表面平滑,皮膚皮紋完整,完全無潰爛、結痂或衛星狀病灶(Satellite lesions)。
- 附屬結構: 墨痣表面有終末眉毛(Terminal eyebrow hairs)自然長出,進一步證實其良性本質。
治療過程與手術技術(Management & Surgical Technique)
基於臨床表現,我們確認該病灶為良性皮內痣。因此,我們決定直接進行二氧化碳(CO2)激光氣化切除,無需進行組織病理學檢查。
- 局部麻醉: 於病灶下方注射少量局部麻醉劑。
- 逐層氣化切除: 在 5.0 times 手術放大鏡下,我們精準地逐層氣化墨痣。高倍放大讓我們在整個過程中清晰可見黑素細胞巢(即墨痣的「根部」)。
- 熱能與焦炭管理: 我們持續擦拭拭去碳化殘渣。因此,術中幾乎無焦炭產生,且達到零出血。
- 終點識別: 當達到乾淨、無色素沉著的真皮底層時,我們立即停止氣化。
視覺終點發現(Visual Endpoint Findings)
最終的激光創面形成了一個整齊的凹陷性傷口。最關鍵的是,在傷口底層清晰可見完整且具活性的毛囊球(Hair follicle bulbs)。由於激光未破壞這些深層毛囊結構,我們預計只要防止術後嚴重發炎,眉毛將能完全再生。
術後護理與臨床結果(Post-Operative Care & Clinical Outcome)
為確保二期癒合(Secondary intention healing)達到最佳效果,患者嚴格遵循以下術後護理方案:
- 每日使用消毒液清洗傷口數次,持續 2 週。
- 保持傷口乾燥,並在早期上皮化(Epithelialization)期間嚴格避免接觸水份。
治療結果
傷口透過二期癒合快速復原。在術後 6 至 8 個月內,局部的紅斑逐漸退去,膚色完全恢復正常。最重要的是,所有眉毛均完全重新長出,毫無毛髮缺失。時至今日,殘留的瘢痕幾乎無法察覺。
討論(Discussion)
要成功切除眉毛內的墨痣並取得理想效果,必須在傷口深度控制、毛囊保留以及瘢痕美學之間取得平衡。
首先,醫生必須精準判斷激光創面的深度。如果墨痣延伸過深,以致二期癒合會留下明顯的凹陷性瘢痕,則有必要進行一期縫合(Primary suturing)。
其次,保留毛囊至為重要。若激光氣化破壞了當地的毛囊,二期癒合將會在眉毛內留下永久性的無毛斑塊(禿斑)。在此類過深的病例中,外科醫生應在激光氣化後縫合傷口。一期縫合能將線狀瘢痕巧妙地隱藏於眉毛的自然流向之中。
最後,執業醫生的專業知識直接決定了手術結果。結合皮膚科知識與醫學美容的精細技巧,能讓醫生精準判斷視覺終點、保護脆弱的毛囊,並選擇正確的關閉傷口方法。因此,擁有皮膚專科及醫學美容(例如皮膚臨床醫學碩士及醫學美容碩士)正規深造訓練的醫生,是執行此類精細手術的理想人選。