
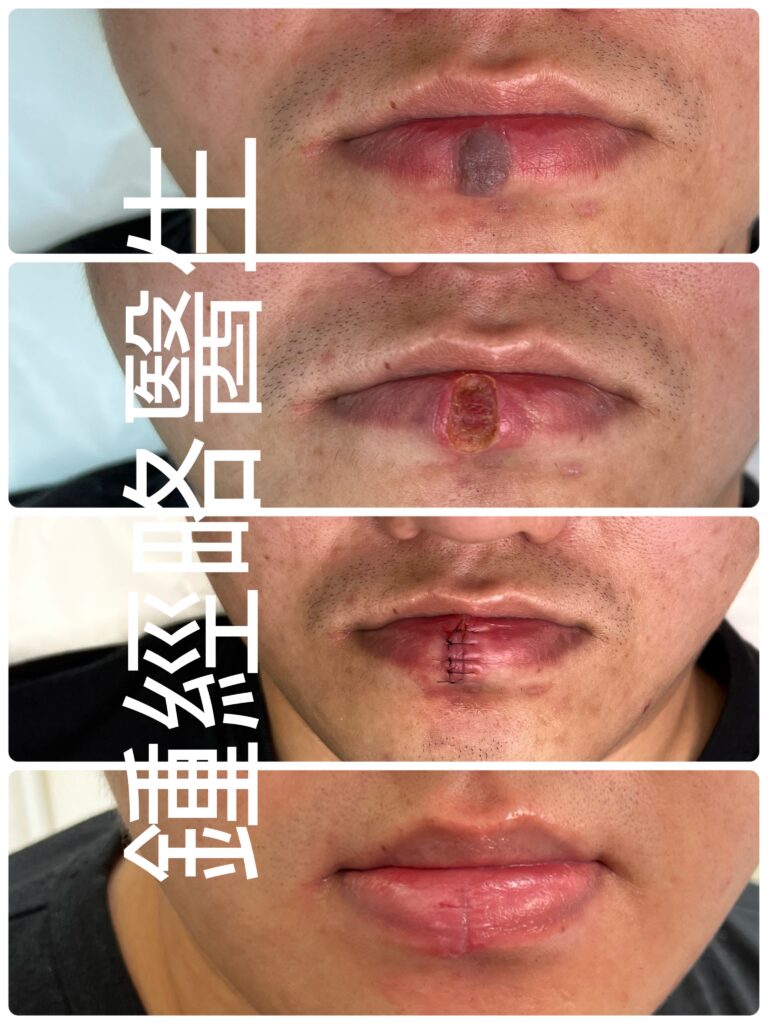
Clinical Discussion: Challenges in the CO₂ Laser Ablation of a Large Benign Melanocytic Nevus on the Lower Lip Vermilion Zone and the subsequent Surgical Closure of the Large Wound
Abstract
Benign melanocytic nevi of the lower lip vermilion present unique anatomical and aesthetic challenges. Because the lower lip is highly vascular and functionally mobile, simple excision or superficial laser ablation risks significant cosmetic defects, wound dehiscence, or secondary infection. Consequently, clinicians must balance complete tissue removal with precise structural repair. This report details the successful treatment of a 1.0cm x 1.5cm benign melanocytic nevus on a 50-year-old male. By combining deep CO2 laser photoevaporation in Ultrapulse mode with layered primary closure, we achieved complete lesion eradication, dynamic stability, and a near-invisible scar.
Case Presentation
Patient History
A 50-year-old male presented with a long-standing, dark pigmented lesion on his lower lip. He reported no significant past medical or family history of dermatological malignancy.
- Duration: The lesion had remained stable for over 30 years.
- Evolution: He observed no changes in size, shape, elevation, or color.
- Symptomatology: The lesion was completely asymptomatic, with no bleeding, ulceration, pain, or pruritus.
- Chief Complaint: The patient requested complete removal solely for aesthetic improvement.
Physical Examination
During the clinical examination, we observed:
- Lesion Profile: A well-demarcated, uniformly pigmented, non-ulcerated nevus measuring 1.0 cm wide and 1.5 cm high.
- Anatomical Extension: The lesion covered the full vertical height of the lower lip vermilion zone. It extended from the wet-dry mucosal junction down to the vermilion border and adjacent cutaneous lip.
- Diagnosis: We diagnosed a benign dermal melanocytic nevus. Furthermore, dermatoscopy revealed no signs of malignant transformation.
Anatomical & Technical Challenges
Removing a 1.0 cm x 1.5 cm lesion from the lower lip presents several distinct hurdles:
- Defect-to-Anatomy Ratio: First, removing a 1.5 cm vertical span effectively splits the lower lip vermilion into separate left and right segments. Leaving this deep defect open to heal by secondary intention severely impairs basic oral functions like eating and speaking.
- Vascularity & Hemostasis: Second, the labial arteries supply abundant blood to the lip. As a result, cold-knife excision without extensive cautery risks heavy intraoperative and postoperative bleeding.
- Infection Risk: Third, the lower lip constantly encounters saliva, food particles, and oral bacteria. Therefore, an open mucosal wound creates a high risk for localized infection.
- Vermilion Alignment: Finally, the lower lip vermilion border serves as a prominent facial landmark. Even a 1 mm misstep across this border creates a visible cosmetic defect. In addition, routine facial movements put continuous tension on the wound, which encourages scar widening.
Surgical Procedure & Methodology
Primary surgical excision would have required wide safety margins and produced an unnecessarily large defect. Instead, we chose a hybrid approach: high-precision CO2 laser ablation followed by primary layered suture closure.
                    [ 1.0 cm x 1.5 cm Nevus Removal ]
                                   │
              ┌────────────────────┴────────────────────┐
              ▼                                         ▼
   [ CO₂ Laser Ultrapulse ]                 [ Layered Primary Closure ]
   • Precise layer-by-layer                 • Deep buried dermal sutures
     photoevaporation                         (Absorbable, tension reduction)
   • Visual clearance of nevus roots        • Non-absorbable 5-0 nylon
   • Simultaneous hemostasis                  for fine surface alignment
1. High-Precision CO2 Laser Ablation
- Laser Mode: We operated the CO2 laser in Ultrapulse mode. This setting delivers high peak power in microsecond pulses, which vaporizes tissue instantly while minimizing heat damage to surrounding tissue.
- Ablation Depth & Visualization: Next, we vaporized the nevus layer by layer under high magnification. We clearly visualized the deep melanocytic “roots” in the dermis during evaporation. We stopped the laser immediately once we cleared all deep roots.
- Hemostasis: Simultaneously, the $10,600 nm wavelength sealed micro-vessels across the ablated bed. Consequently, we achieved a completely bloodless field during and after the ablation.
2. Surgical Reconstruction & Layered Closure
Even though the laser prevented immediate bleeding, leaving a 1.5 cm vertical defect open remained unsafe. Therefore, we immediately performed a primary reconstructive closure:
- Deep Dermal Layer: First, we placed buried deep dermal sutures using absorbable material. This step closed dead space, reinforced the wound, and relieved tension on the skin edges.
- Surface Alignment: Afterwards, we closed the superficial layer with 5 interrupted 5-0 nylon sutures. We aligned the vermilion border precisely to prevent any stepping or displacement.
Postoperative Course & Clinical Outcome
Postoperative Care Protocol
- Wound Care: We instructed the patient to clean the lip frequently with sterile water and chlorhexidine solution. Afterwards, he applied sterile Vaseline continuously to shield the wound from oral bacteria.
- Functional Advice: In addition, the patient avoided wide mouth opening and exaggerated facial movements for the first two weeks.
- Prophylaxis: We kept oral antibiotics in reserve to initiate at the first sign of infection.
Results
- Suture Removal: Because the lower lip undergoes constant movement, we left the surface nylon sutures in place for 3.5 weeks to prevent micro-dehiscence.
- Immediate Scar Evaluation: Upon suture removal at week 3.5, we observed:
- Apposition: The vermilion border aligned near-perfectly with zero stepping or displacement.
- Scar Quality: The site showed minimal suture marks. Overall, the linear scar remained flat, soft, and barely noticeable against the natural mucosal texture.
- Complications: The patient experienced no bleeding, no infection, and maintained full oral function.
Clinical Takeaways
- Utility of CO2 Ultrapulse Laser: First, the Ultrapulse mode offers exquisite depth control on vascular mucosa. It allows complete removal of benign tissue under direct vision without damaging healthy surrounding structures.
- Mandatory Primary Closure: Second, clinicians must suture large mucosal defects even if laser ablation yields a dry wound bed. Deep dermal tension-reducing sutures are essential to withstand the strong forces of the orbicularis oris muscle.
- Extended Suture Retention: Finally, high-tension mucosal sites benefit from extended suture support. Leaving sutures in place longer allows the deep dermis to mature before full mechanical movement resumes.
臨床討論:下唇唇紅區大型良性色素痣之 CO₂ 激光氣化與手術縫合挑戰
摘要
下唇唇紅區的良性黑色素痣(Melanocytic nevi)在臨床處置上,向來具備獨特的解剖與美學挑戰。由於下唇血管極為豐富,且日常動態活動頻繁,因此若單純進行傳統切除或淺層激光氣化,極易引致顯著的面部缺陷、傷口裂開或繼發性感染。基於上述考量,臨床醫生必須在「完整清除病灶」與「精準結構修復」之間取得平衡。本文詳細記錄一例位於 50 歲男性下唇、大小為 1.0 cm×1.5 cm 的良性黑色素痣成功案例。我們特別結合了深層 CO2 超脈衝激光氣化(Ultrapulse mode) 與 分層一期縫合技術,進而成功實現病灶完全清除、維持動態穩定,並達到近乎無痕的理想預後。
案例呈現
病患病史
一名 50 歲男性因下唇長期存在深色色素痣前來求診。在病史方面,患者無顯著既往病史,亦無皮膚惡性腫瘤之家族病史。
- 病程時間: 病灶已存在超過 30 年,期間情況相當穩定。
- 演變情況: 經過長年觀察,其大小、形狀、凸起程度及顏色均無顯著改變。
- 臨床症狀: 此外,病灶完全無症狀,無自發性出血、潰瘍、疼痛或瘙癢。
- 主訴需求: 最終,患者出於純粹的美觀考量,主動要求完全去除病灶。
理學檢查
於臨床檢查期間,我們觀察到:
- 病灶特徵: 病灶為一個邊界清晰、顏色均勻且無潰瘍的良性痣,測量大小為 寬 1.0 cm× 高 1.5 cm。
- 解剖延伸: 在位置上,病灶覆蓋了下唇唇紅區(Vermilion zone)的整個垂直高度,從上方的乾濕黏膜交界處,一路向下延伸至唇紅緣(Vermilion border)及鄰近的唇部皮膚區。
- 臨床診斷: 綜合評估後診斷為良性真皮黑色素痣。同時,皮膚鏡檢查未發現任何惡性變化的徵象。
解剖與技術挑戰
若要從下唇完整清除一個 1.0 cm×1.5 cm 的病灶,臨床上必然會面臨以下幾項明確的難題:
- 缺陷與解剖比例:首先,去除 1.5 cm 的垂直範圍,實際上會將下唇唇紅區分割成獨立的左右兩半。倘若任由這個深層缺陷以二期癒合(Secondary intention)方式自行修復,隨之而來的將是嚴重損害進食與說話等基本口腔功能。
- 血管分佈與止血:其次,唇動脈為嘴唇提供極為豐富的血供。因此,若採用冷鋼刀直接切除而無電灼止血,術中及術後大出血的風險極高。
- 感染風險:再者,下唇日常會持續接觸唾液、食物殘渣及口腔細菌。這意味著,開放性的黏膜傷口會造成極高的局部感染風險。
- 唇紅緣對齊:最後,下唇唇紅緣是極其重要的面部美學標誌。即使跨越該邊界僅出現 1 mm 的微小錯位,也會造成肉眼可見的缺陷。此外,日常面部表情運動會對傷口產生持續張力,進一步拉寬疤痕。
手術過程與方法
鑑於傳統的一期手術切除需要保留較寬的安全邊緣,從而會製造出不必要的大型缺陷;因此,我們選擇了複合式方案:高精準度 CO2 激光氣化,隨後緊接進行一期分層縫合。
                    [ 1.0 cm x 1.5 cm 墨痣清除 ]
                                   │
              ┌────────────────────┴────────────────────┐
              ▼                                         ▼
   [ CO₂ 超脈衝激光 (Ultrapulse) ]            [ 一期分層縫合重建 ]
   • 精準逐層氣化病灶                         • 深層埋線縫合 (可吸收線,減張)
   • 直觀清除黑色素痣「根部」                  • 5-0 尼龍線進行表層精細對齊
   • 同步凝血止血
1. 高精準度 CO2 激光氣化
- 激光模式: 我們將 CO2 激光設定為 超脈衝模式(Ultrapulse mode)。此設定能在微秒級脈衝內釋放高峰值功率,不僅能瞬時氣化組織,更能將對周圍組織的熱傷害降至最低。
- 氣化深度與顯微觀察:接著,我們在高倍放大下逐層氣化病灶。在氣化過程中,機能清楚觀察到位於真皮層深處的黑色素痣「根部」(黑色素細胞巢)。一旦徹底清除所有深層根部後,便即刻停止激光操作。
- 止血效果:與此同時,激光的 10,600 nm 波長發揮了優秀的凝血作用,有效封閉氣化底部的微血管。結果,我們在術中及術後均獲得了完全無血的清晰視野。
2. 手術重建與分層縫合
儘管激光成功阻止了即時出血,但留下一道 1.5 cm 的垂直缺口依然極具風險。為此,我們隨即進行了一期重建縫合:
- 深層真皮層(減張):首先,我們使用可吸收縫線進行深層埋線縫合。藉由這個步驟,消除了死腔(Dead space)並鞏固傷口,從而徹底釋放了皮膚邊緣的張力。
- 表層對齊:隨後,我們使用 5 針獨立的 5-0 尼龍線 精細縫合表淺層。過程中特別注意精確對齊唇紅緣,以防止出現任何階梯狀錯位(Stepping)。
術後護理與臨床結果
術後護理方案
- 傷口護理: 我們指示患者需定期使用無菌水與 氯己定(Chlorhexidine)消毒液 清潔嘴唇。清潔過後,需持續塗抹無菌 凡士林(Vaseline),藉此構建屏障以阻絕口水及口腔細菌侵入傷口。
- 功能性建議:此外,我們建議患者在術後前兩週應儘量避免大張嘴及誇張的面部表情。
- 預防性措施:另一方面,我們亦備妥了口服抗生素,以便在出現早期感染徵象時能立即介入處置。
臨床結果
- 拆線時間:考慮到下唇需經歷頻繁的動態運動,我們將表層尼龍線保留了 3.5 週,目的在於防止傷口出現微裂(Micro-dehiscence)。
- 拆線即時疤痕評估:於第 3.5 週拆線時,我們觀察到以下顯著成果:
- 對齊狀況: 唇紅緣達成了近乎完美的對齊,完全沒有出現錯位或階梯狀斷層。
- 疤痕質量: 針眼痕跡極為輕微;整體而言,線狀疤痕平整且柔軟,自然地與下唇黏膜紋理融為一體,肉眼幾乎難以察覺。
- 併發症:同時,患者未出現任何出血或感染,並完全保留了嘴唇的口腔功能與感覺。
臨床要點
- CO2 超脈衝激光的應用價值:首先,超脈衝模式在富含血管的黏膜上展現了極佳的深度控制能力。這使得醫生能在直視下完全去除良性組織,同時又不傷害周圍的健康結構。
- 大型黏膜缺陷必須進行一期縫合:其次,即便激光氣化創造了無血的傷口床,臨床醫生仍必須對大型黏膜缺陷進行縫合。尤其深層真皮減張縫合更是抵禦口輪匝肌(Orbicularis oris muscle)強大張力的關鍵所在。
- 高張力部位需延長留線時間:最後,高張力與高活動度的黏膜部位確實能從延長縫線支持中獲益。適度延長留線時間,將有助於讓深層真皮在完全恢復機械運動之前,達成更為充分的成熟與癒合。